What Dental Fear Does To The Body In The Chair
By Arpan Nalin Patel, D.M.D.

A patient sits down and the pulse reading is already higher than it was in the waiting room ten minutes earlier. Nothing has been picked up, nothing has been explained, and the body has already decided what kind of hour this is going to be. This is written for people who have been told their dental fear is something to get over, and for clinicians who have watched a routine appointment turn difficult for reasons that were never on the schedule.
What Happens In The Body When A Patient Is Afraid
Fear is a physical event before it is anything else. Adrenaline moves through the system, the pulse climbs, breathing turns shallow and fast, and blood is redirected away from the surface of the body toward the large muscles. The National Institute of Mental Health describes the same cascade in anxiety more broadly, and a treatment room is simply one of the places it fires.
Salivary flow drops, so the mouth goes dry. Muscles in the jaw and the neck tighten and then hold that tension rather than releasing it. Pupils widen, and ordinary sounds arrive louder than they are.
The setting makes that response easy to set off. A patient is lying back, cannot see what is happening above them, cannot speak while it happens, and has someone working inside their airway at a closeness no ordinary social situation allows. Very little else in adult life combines those four things at once.
It explains why a person who is calm through a medical procedure can be undone by a cleaning. The body is not ranking procedures by how serious they are. It is responding to the position, the noise and the temporary loss of any way to say stop.
A patient in that state is not being difficult. They are running a program built for a real threat, and that program does not draw a fine distinction between a predator and a handpiece.
How Fear Changes The Way An Appointment Runs
Every one of those changes carries a clinical consequence. A dry mouth makes isolation harder and makes scanning and impressions less comfortable. A tight jaw limits opening and tires within minutes, which shortens the working window before the patient needs a rest.
Rapid shallow breathing makes the gag reflex more active, which changes what can be reached at the back of the mouth. Raised blood pressure and inflamed tissue together mean more bleeding during scaling or surgery, so the field is harder to see. The library of oral health topics kept by the American Dental Association sets out the clinical background to most of these procedures for anyone who wants to read it beforehand.
Time is the consequence nobody schedules for. An appointment that takes forty minutes with a settled patient takes closer to an hour with a frightened one, because the rests are real rests and the explanations get repeated. A room that books both at the same length has quietly decided that one of them will be rushed.
The largest effect, though, is on attention. A patient in a heightened state retains very little of what is said to them, which is why an explanation given at the start of a difficult appointment usually has to be given again afterward. None of this is a question of willpower.
Fear is not a mood a patient carries into the room. It is a set of physical changes that alter what can actually be done in the next forty minutes.
What Reduces The Physical Response In The Chair
Because the response is physical, the things that reduce it are physical and procedural rather than reassuring. Predictability is the strongest of them. A patient who knows the order of the next four steps has less to brace against, and bracing is what drives most of the muscular part of this.
Pacing matters nearly as much. Short segments with planned pauses let the nervous system settle before the response stacks on itself, and a stacked response is far harder to bring down than a fresh one. The pause is treatment time rather than lost time.
A first visit with nothing done is a legitimate use of a room. Records, a look, a conversation and nothing sharp at all gives the nervous system an appointment that ended without incident, and that is the first entry in a pattern the body will read later. Patients who have avoided treatment for years often need that visit more than they need the treatment itself.
Control matters most. A signal that stops the appointment, agreed in advance and honored every single time without exception, turns a situation the patient is enduring into one they are taking part in. The American Dental Association keeps patient information on dental anxiety that covers the same ground for people who would rather read it at home than hear it in the chair.
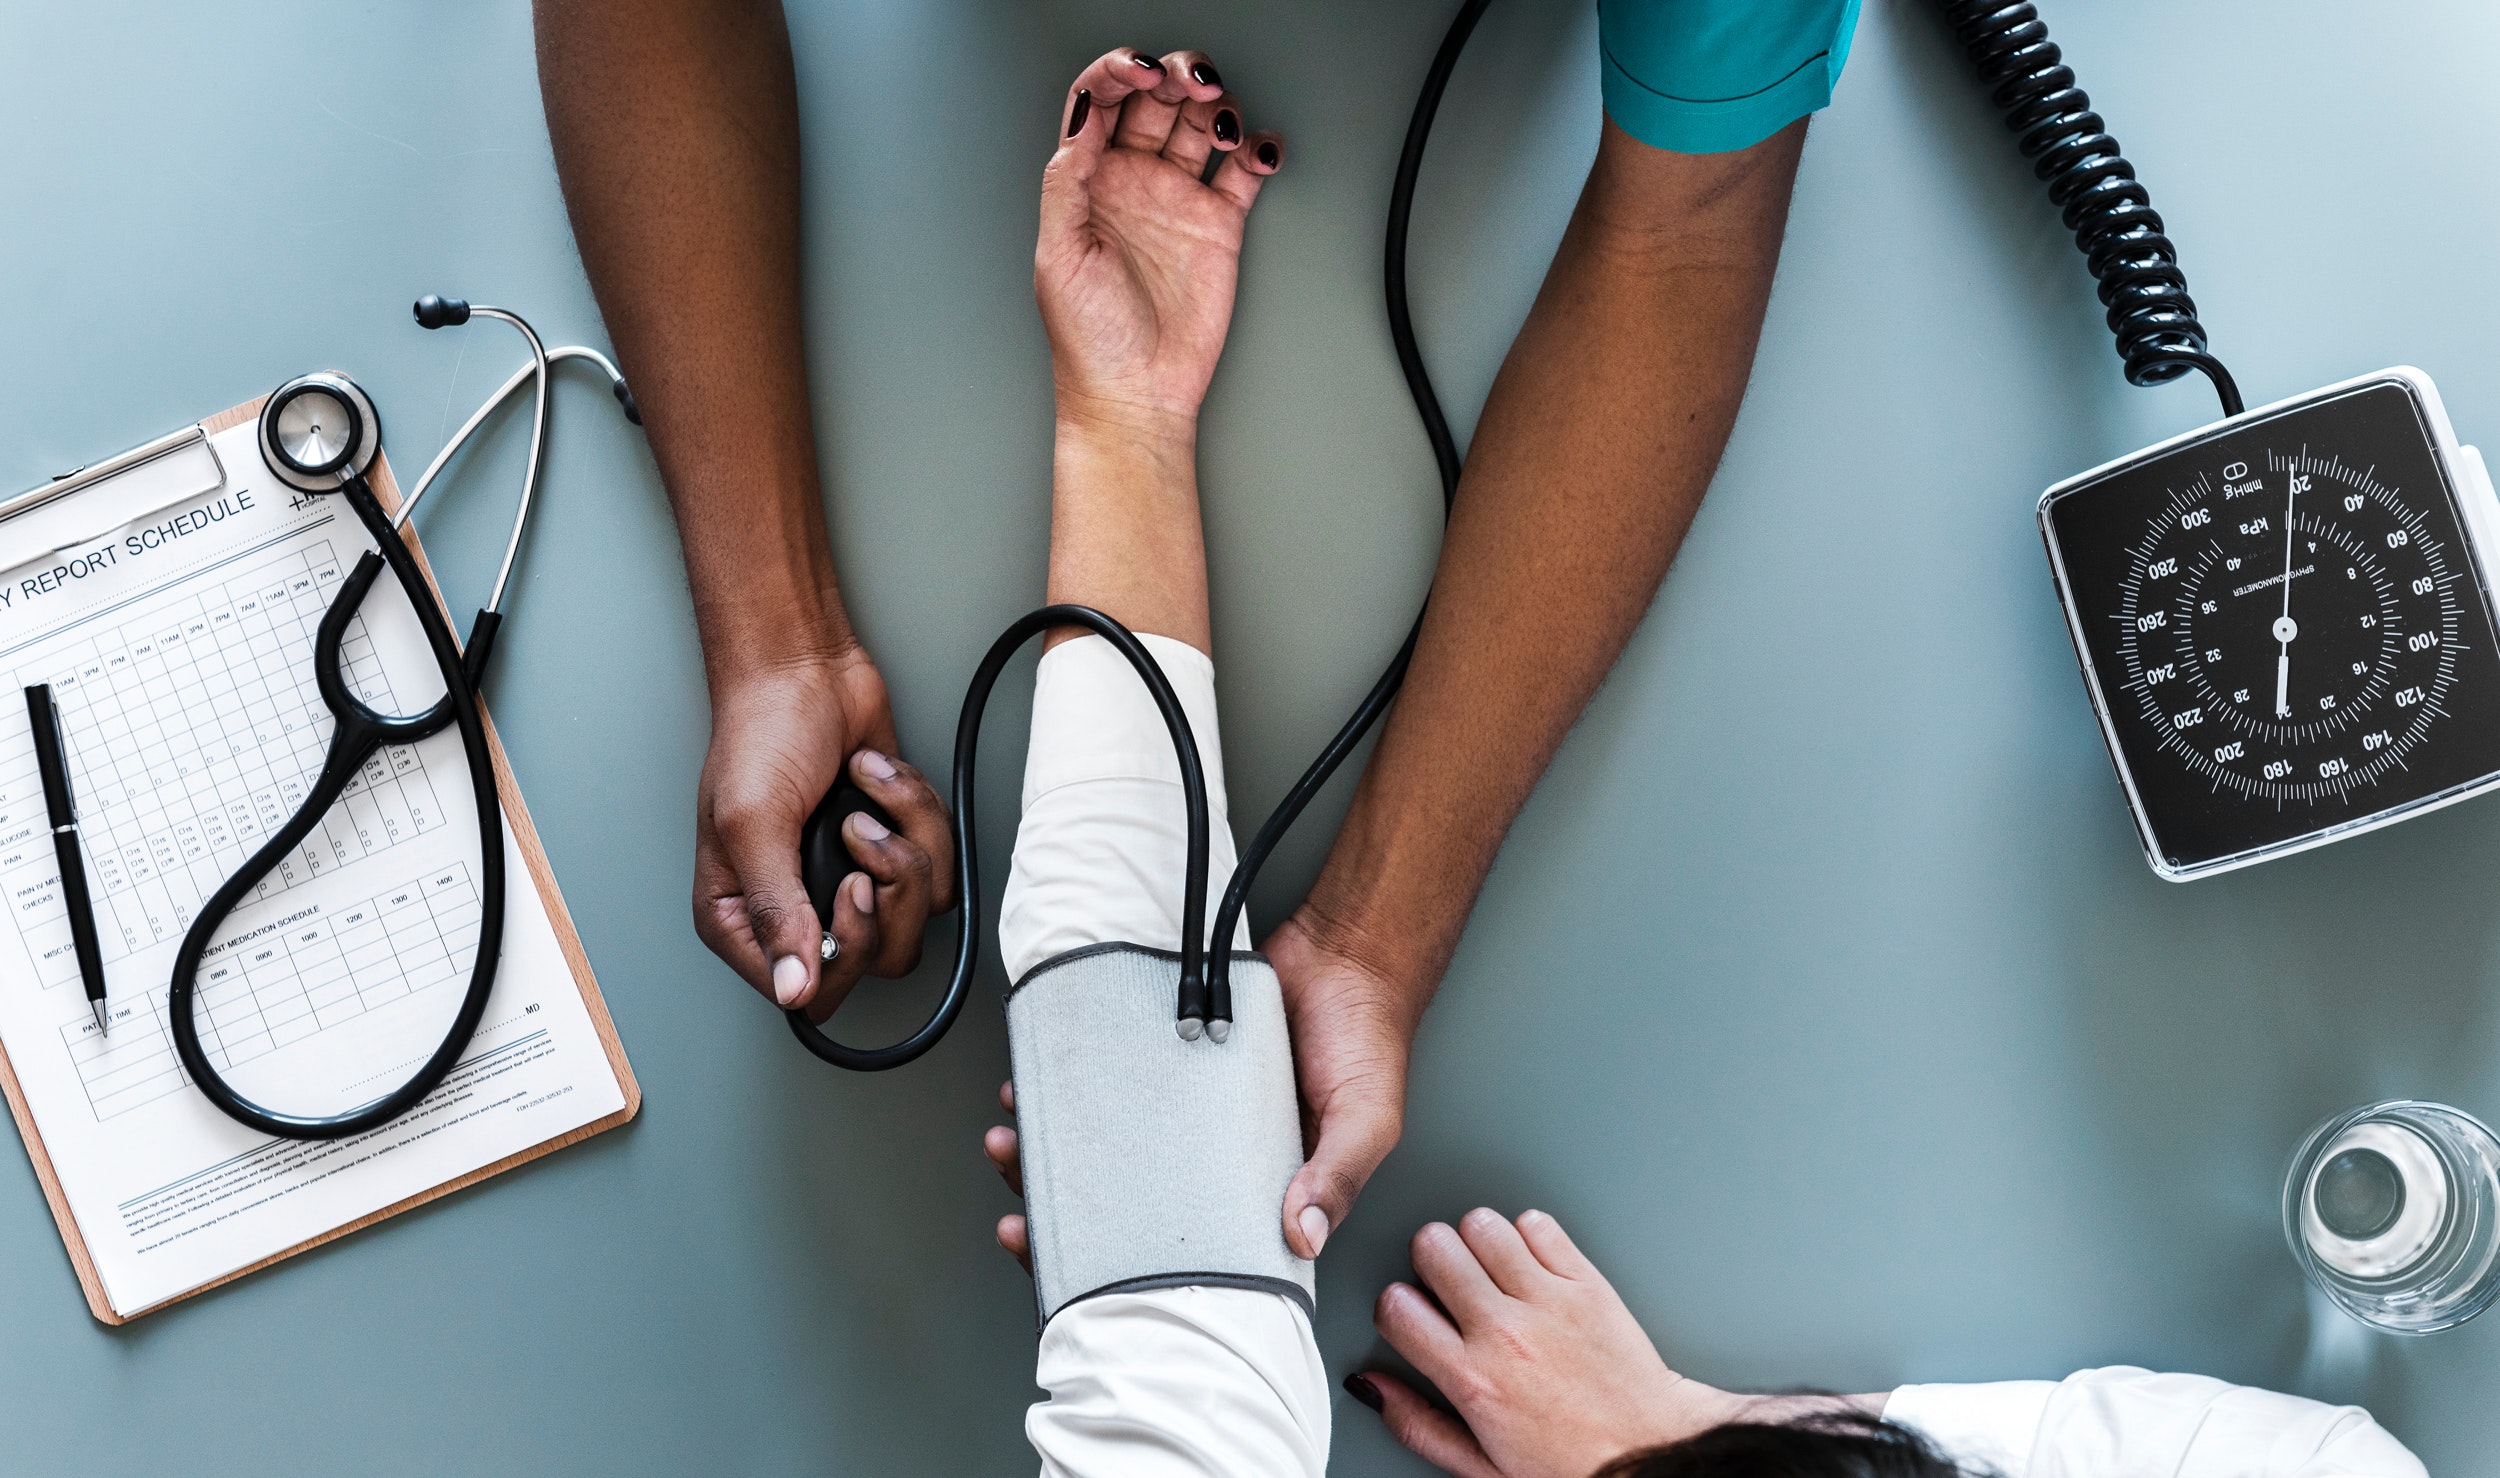
A baseline pulse and blood pressure reading taken at the start earns its place for a reason beyond safety. It produces a number that can be taken again forty minutes later, and a number that has come down is more persuasive to a frightened person than any sentence available to me. Medication has a role here too, and what happens before and after a sedation appointment is a subject of its own.
The Part That Does Not Resolve In One Appointment
Here is the honest caveat, and it is the reason any of this is worth writing down. Naming the physiology out loud helps some patients a great deal and makes others measurably worse.
For many people, hearing that a racing pulse is an ordinary reflex rather than a personal failing is a relief, and the reading falls within a minute of being told. For others, attention drawn to the body is exactly the wrong direction, and describing the heart rate simply makes them aware of the heart rate. There is no reliable way to know in advance which person is sitting in front of me.
What works is to offer the explanation once, briefly, and then read what happens next. A patient who leans in gets the rest of it. A patient who tightens gets a change of subject and a slower pace instead.
The response also does not switch off at the door. Adrenaline clears slowly, and patients frequently describe being tired for the rest of the day after an appointment that went perfectly well by every clinical measure. Telling someone that in advance keeps them from reading ordinary fatigue as a sign that something went wrong.
The second honest thing is that one good appointment does not undo the response. The body learns safety the way it learns everything else, through repetition, so three uneventful visits change more than a single well managed one ever will. A patient whose pulse at the fourth visit matches the first has been managed rather than helped.
For a reader who has been putting this off, the useful part is the last one. The way the body behaves in that chair is ordinary physiology, shared with everyone who has ever been frightened of anything at all. It is information a clinician can work with rather than evidence of a character flaw, and it belongs in the conversation at the start of an appointment in the same way a medical history does.
A room built around that fact runs differently. The order is explained, the pauses are planned, the stop signal is real, and the pace follows the person rather than the schedule.
The physiology does not need to be argued with. It needs to be given less to react to.
Arpan Nalin Patel, D.M.D., practices dentistry in lower Bucks County, Pennsylvania.


